
General operational information only. Payer, state, contractual and regulatory requirements vary. Confirm current requirements with the applicable payer or agency.
Quick answer
What practice leaders need to know
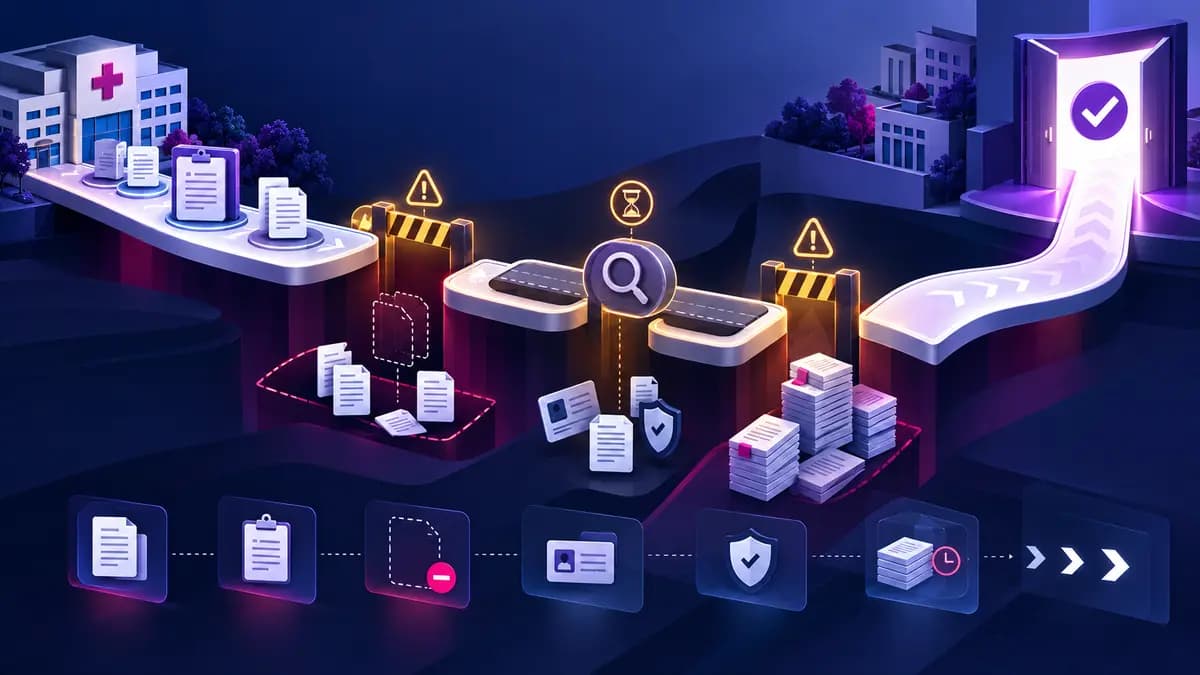
Credentialing commonly stalls because records conflict, the application is incomplete, the provider-group relationship is unclear, payer requests are unanswered, or follow-up is reaching the wrong department. The tracker should show the exact blocker, supporting evidence, responsible party, last contact, next action and follow-up date. Separate practice-controlled gaps from payer processing, contracting and system-loading delays so leadership can act without promising a decision date controlled by a third party.
Credentialing delays are not all the same
Some delays are controlled by the payer, while others begin with incomplete provider information, inconsistent practice records or missing follow-up. The first step is separating a payer processing delay from an application that is incomplete, misrouted or waiting on a practice dependency.
Start with one verified source of information
Legal names, addresses, ownership, licenses, taxonomy selections and identifiers should match across the application, CAQH, NPPES and supporting records where applicable. A structured intake process reduces preventable rework before submissions begin.
Reporting should show more than submitted
A useful credentialing report identifies the payer, provider, submission date, current status, reference information, open dependency and next follow-up date. Practices should be able to see where each application stands without repeatedly asking for an update.
Plan for enrollment after approval
Credentialing approval does not always complete EDI, ERA, EFT, portal, directory or billing setup. A connected plan should confirm the effective date and the remaining steps required before claims and payments can move correctly.
Separate waiting from blocked
An application can be within normal processing, waiting for committee review, blocked by missing information or sitting in the wrong department. Record the payer's stated stage and evidence. Calling every open item pending hides which applications need action.
Escalate with a complete history
Bring the submission date, confirmation number, provider and group identifiers, location, product, reference numbers and requested documents. Ask for the current department, exact blocker and next step, then record the representative and follow-up date.
Check whether the payer is accepting applications
Before preparing a full packet, confirm the exact network, product, provider type and geography and whether the payer is accepting applications. A closed panel, limited network need or ineligible provider type is different from a delayed credentialing review. Record the source and date and ask whether an interest form, exception or future review path exists. Payers control network participation decisions, so avoid promising acceptance. A practice can still evaluate other payer and patient-access options while preserving accurate information about the target network.
Resolve identity mismatches at the source
Compare legal names, professional names, NPIs, taxonomy, tax records, licenses, addresses, CAQH and payer applications. Determine which value is authoritative before changing anything. Correct NPPES, CAQH, PECOS or other systems through their own processes; updating one does not automatically update another. Avoid sending different explanations to multiple payers for the same unresolved discrepancy. Maintain a change log with old and new values, effective dates, affected records and confirmation. Identity inconsistencies can cause requests at intake, verification, contracting and claim loading, so a source correction prevents more than one delay.
Distinguish an incomplete application from payer processing
A file may be received but incomplete, complete and awaiting review, routed to another department, pending committee, waiting for contracting or technically approved but not loaded. Ask the payer for its actual status language and the exact outstanding requirement. Preserve the confirmation and reference. Do not reset the follow-up clock by resubmitting a complete packet unless the payer directs it; duplicate applications can create multiple records. The tracker should show whether the next action belongs to the practice, provider, payer or another third party.
Monitor every communication channel
Payer requests may arrive through email, portals, fax, mail or a credentialing platform. Use monitored addresses and named portal access with a backup owner. Route time-sensitive notices into the tracker and acknowledge receipt when appropriate. Remove former staff access and update contact information after personnel changes. A complete application can stall when a clarification request sits in an unmonitored inbox. Do not share provider passwords to preserve continuity; use supported roles and delegated access and maintain an internal escalation path when the responsible person is unavailable.
Answer requests from a verified source record
When the payer asks for a missing document or clarification, compare the request with the controlled provider and practice record. Confirm that the response is current, complete and consistent with other applications. If the request reveals an underlying error, correct that record first and identify every submission affected. Retain what was sent, when, by whom and through which channel. Sending a fast one-off answer may move one file temporarily but create another discrepancy in CAQH, NPPES or a second payer application.
Clarify group affiliation and roster work
An individual provider can be credentialed while the payer has not linked the provider to the billing group, tax entity, location or product. Ask whether a separate roster, affiliation, reassignment or contract action is pending and which department owns it. Confirm the provider and organization NPIs, tax identification number, service address and requested effective date. Treat individual approval and group billing readiness as separate evidence. This distinction is essential when the provider changes practices or the organization adds a location; a prior approval does not automatically establish the new relationship.
Track contracting after credentialing review
The payer's qualification review may be followed by contract negotiation, signature, countersignature, system loading and effective-date confirmation. Record each stage and the responsible party. Have qualified legal or financial advisors review material contract terms and fee schedules where appropriate. Do not schedule based solely on a verbal statement that credentialing passed when the participation relationship is incomplete. Some payer workflows combine stages and others separate them, so the tracker should reflect the payer's actual process rather than impose one universal sequence.
Verify the effective date and loaded record
When approval arrives, read the notice for the provider, entity, location, network or product and effective date. Confirm any remaining affiliation, directory, portal or billing setup. Payers control retroactivity and correction processes; do not infer the date from submission or committee review. Give scheduling and billing teams the written verified status and make uncertainty visible. An application can appear complete to credentialing while claims still reject because the payer's claim system has not loaded the relationship or uses a different effective date.
Use purposeful follow-up intervals
Follow the payer's stated processing window and any material deadlines, but do not let normal processing become an indefinite pending status. Set the next follow-up date based on the payer's response, current stage and risk. Each contact should ask a precise question and record the result. Escalate when the payer cannot locate the file, requests the same material repeatedly, misses its stated window or provides conflicting effective-date information. Repeated calls without a new question or evidence add activity but not movement.
Report controllable and external delays separately
Leadership needs to see whether a delay is caused by missing provider information, internal approval, portal access, payer review, network availability, contracting, third-party verification or system loading. Show the affected provider, payer and launch dependency, owner, evidence and next action. This prevents teams from blaming the payer for a practice-controlled gap or promising a date controlled by an outside organization. Use trend data to improve intake and follow-up, while communicating third-party uncertainty honestly in staffing, scheduling and revenue forecasts.
Use a complete escalation packet
When ordinary follow-up fails, assemble the submission confirmation, application copy, provider and entity identifiers, location, network product, reference history, requested documents and the precise outcome needed. Route it through the payer's credentialing, provider-relations or other designated escalation channel. Keep the request factual and distinguish receipt, review, contracting, loading and effective-date questions. Record the escalation date, recipient and next follow-up. A complete history makes it easier for a new payer representative to act and prevents the practice from restarting the explanation on every contact.
Plan operational contingencies
If enrollment is delayed, leadership should decide how scheduling, patient communication, self-pay or out-of-network options and launch timing will be handled with qualified legal and financial guidance. Do not let front-desk staff infer participation from a pending application or verbal estimate. Communicate only verified status and document approved policies. A contingency plan protects patients and the practice without pressuring credentialing staff to promise a third-party decision date. Update the plan when the payer supplies new evidence or the effective date changes.
Review the process after resolution
When a stalled file moves, document the actual cause and which action resolved it. Determine whether the event was isolated or signals a weakness in intake, source data, access, payer routing, follow-up or affiliation management. Update the checklist or payer matrix only after the lesson is verified. Measure repeated causes and deadline risk across the portfolio. A resolved application still provides valuable information: without a short retrospective, the next provider may encounter the same preventable delay.
Give leadership a decision-ready summary
A useful status report names the affected provider, entity, location and payer product; the verified stage; the last completed action; the current dependency; the responsible party; and the next dated action. Add revenue or scheduling exposure when it can be supported. This format lets leaders make an operational decision without interpreting a long email chain and prevents the word pending from hiding materially different risks.
Working reference
Credentialing delay diagnostic
Use documented payer information rather than estimated status labels.
| Observed status | Question | Next action |
|---|---|---|
| No application found | Was it received under the correct entity and channel? | Verify evidence and routing |
| Incomplete | Which exact field or document is missing? | Correct the source record and respond |
| Provider not linked | Was affiliation or roster action completed? | Submit or correct the relationship |
| Committee review | Is anything outstanding before review? | Confirm schedule and follow-up |
| Approved, not billable | Are contract, effective date or system loads incomplete? | Verify downstream activation |
Common questions
Questions practice teams ask
How long should credentialing take?
Timelines vary by payer, provider type, market and readiness. Use the payer's current estimate and documented status.
Should every payer use the same status labels?
No. Track the payer's actual stage, blocker and next action.
What if the payer cannot find the application?
Use submission confirmation and identifiers to verify receipt, routing and entity.
Does approval mean claims can be submitted?
Not always. Confirm contract, effective date, affiliation and billing readiness.
When should leadership be alerted?
Escalate deadline risk, repeated requests, unavailable networks, effective-date concerns and files without an accountable next step.
Primary references
Sources and further reading
Requirements can change. Use these primary sources to confirm the current rule that applies to the payer, service and date of care.
Ready to turn this guidance into action?
Tell us what is happening in your practice, and we will help you identify the most useful next step.